 LEN
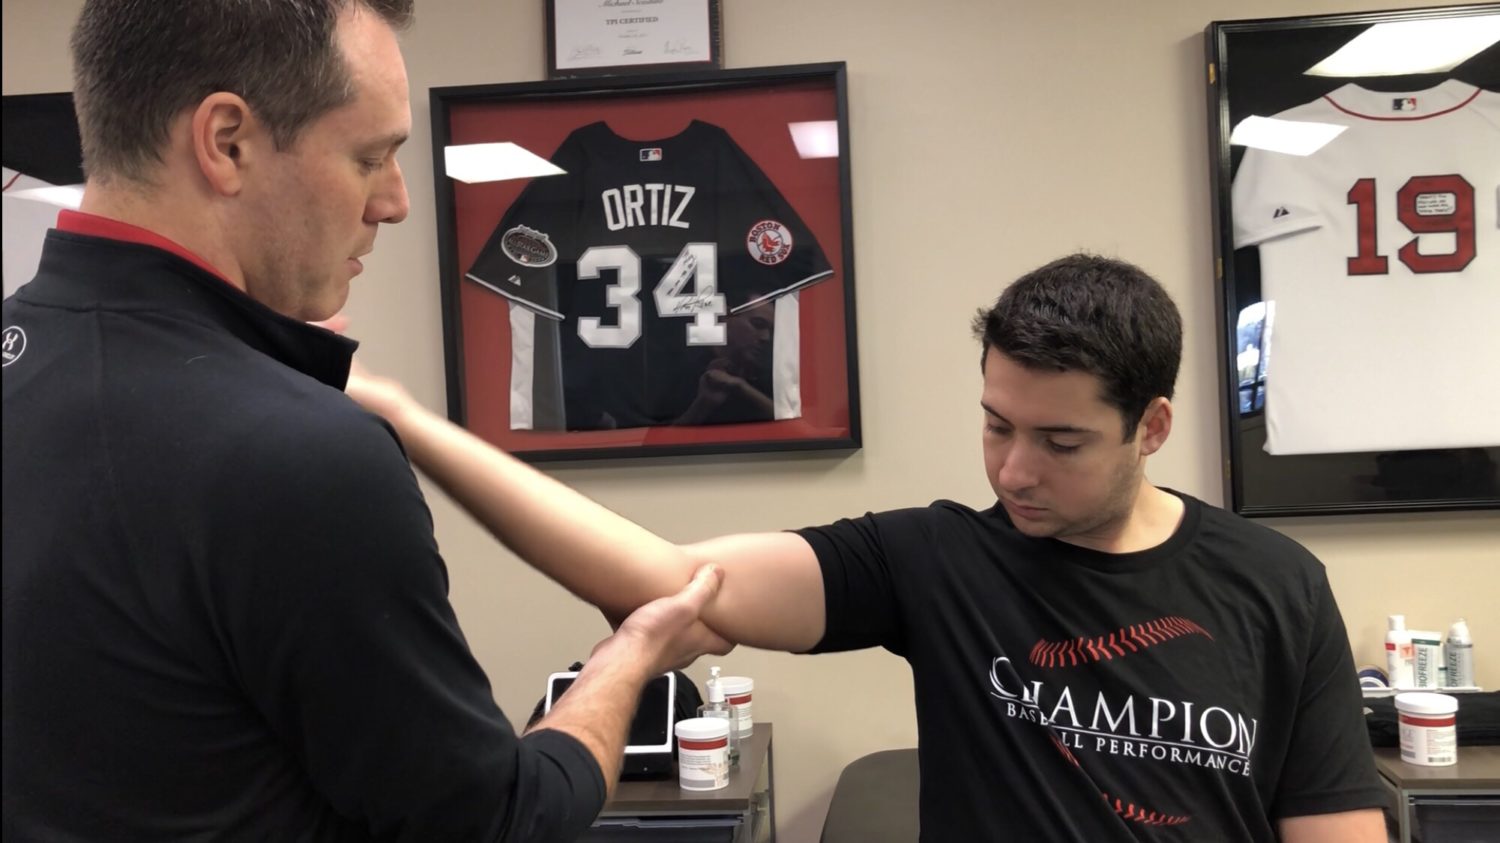
I have assessed hundreds if not thousands of elbows for various injuries. One of the most common ailments that I see in my practice is a UCL (ulnar collateral ligament) sprain, aka ‘Tommy John ligament’, especially in a baseball player. This post discusses the typical presentation of a UCL sprain, testing the elbow for a UCL sprain and how I rule in/out with a few simple tests.
Factors contributing to UCL sprains
Injuries to the elbow UCL continue to grow due to many factors. Some think it may be due to:
- current training regimens,
- sports specialization,
- overuse/fatigue,
- weighted ball training or
- increased velocity.
(Seems like a great outline for future blog posts!)
Whatever the thought, the clinician needs to be able to differentially diagnose the issue and come up with a game plan that meets the goals and desires of the athlete. No algorithm is going to fit perfectly into each individual’s current/future baseball plans.
That’s why I carefully consider each factor and review it with my baseball players so we can come up with a good game plan in case they get diagnosed with the dreaded UCL sprain!
The Typical UCL Story
Most of the pitchers that come to me with elbow pain have a similar story… and it’s probably not what you would think. Often times, it’s not a dramatic blowout where the ball goes flying into the stands while the pitcher is writhing in pain. Most commonly, it’s a slow onset of elbow soreness, loss of velocity and/or location, or tingling into their fingertips.
The epidemic of Tommy John injuries has freaked out most pitchers. They automatically think they’ve blown their elbow out if they even feel a slight hint of pain or soreness.
It’s up to the clinician to determine what structures may be involved and to have a firm plan in place that allows for a gradual return to throwing or to refer out to a surgeon that you trust.
Unfortunately, it’s not always clear-cut. We need to be able to sift through the stories and recognize that there are many potential causes for elbow pain in a baseball player.
Differential Diagnosis
There are many structures that could become injured in a baseball pitcher. Let’s quickly run through the most common injuries and give my thoughts on each:
- Flexor-pronator strain– often accompanies a UCL sprain because static stability compromised; painful resisted wrist flexion and sometimes extension. Palpable tenderness in muscle belly not close to the UCL insertion (sublime tubercle.) Often pain-free UCL special tests.
- Loose bodies: pain-free UCL special tests, pain with late follow-through phase of throwing; significant posterior elbow pain with bounce home test that replicates their symptoms
- Ulnar neuritis: tingling in the 4th-5th fingers (ring and pinkie fingers); often accompanies a UCL sprain due to increased medial elbow laxity; rarely an isolated event in my opinion.
- Little Leaguer’s elbow: younger pitcher/player less than 14 years of age; may have painful UCL tests; pain at similar location but often closer to epicondyle; MRI to confirm; rest for at least 3 months; don’t mess with these (would’ve been a UCL if a couple years older and has a higher propensity for a UCL issue later in life.)
- Thoracic Outlet Syndrome: pain-free UCL tests; loss of control (some call it the yips); vague heaviness and weakness with loss of velocity and location; TOS sees us more than we see it
- Cervical spine: negative UCL tests; need to consider myotomes and dermatomes; not as common in younger-aged baseball players but may be seen in older pitchers
My go-to UCL tests
There are many tests out there but after many years of playing around with lots them, I have narrowed it down to 4 tests that I feel are the best to help diagnose a UCL sprain. Check out the video below.
I go deeper on this in my MedBridge course, Rehab After Tommy John Surgery: Optimizing Return to Throwing. Use code LENNY to save on a yearly subscription.
See the course →UCL Treatment Options
The treatment options will vary case by case and highly dependent on many variables. The clinician and client need to consider:
- How much rest, if any has occurred- should try AT LEAST 4-6 weeks of no throwing and rehab to restore ROM (GH flexion, external rotation, and horizontal adduction) then attempt an ITP if pain-free on the clinical exam.
- Time of year- If it’s the end of the baseball season, may shut it down to give the athlete plenty of time to rest. If clearly needs surgery, plan surgery and rehab, including throwing programs, to last 12-18 months before return to competition.
- Previous injury history- previous history of elbow issues, especially Little Leaguer’s elbow sets off many bells and whistles; had tingling into fingers a previous time but it went away with some rest; Rest may help but usually leans toward surgery.
- Tommy John Surgery- reconstruct the ligament; need at least 9-12 months if a pitcher…the longer the better it seems
- Internal brace UCL repair: repairs the ligament, then reinforces it with a collagen-dipped tape sewn into the joint. Quicker rehab, and we now have good outcome data for the right type of tear (see the update below).
2026 Update: What’s Changed
I wrote this post back in 2018, and a lot has happened with UCL injuries since then. The basics haven’t changed. A good history and a careful exam still tell you most of what you need to know. But a few things are worth adding.
The research behind the moving valgus stress test
If you want numbers behind one of the most studied UCL tests, look at the moving valgus stress test from O’Driscoll and colleagues. In 21 patients who went on to surgery, it was 100% sensitive and 75% specific, with pain peaking around 90 degrees of elbow flexion. It’s a small study, so I use it as part of a cluster of tests, not on its own.
UCL repair now has real outcome data
When I wrote this, the internal brace repair was brand new and nobody had long term results. Now we do. Dugas and colleagues followed competitive athletes at least 2 years out. About 98% of the repair group and 99% of the reconstruction group got back to their sport. The big difference was time. The repair group got back to competition in about 9 months, compared with about 13 months after reconstruction.
Keep in mind repair is only an option for certain tears, mostly when the ligament pulls off the bone at one end. Plenty of pitchers still need a full Tommy John.
Getting back to throwing
Once they’re ready to throw, the program should match the injury. Mike Reinold, Ben Dowling, Glenn Fleisig and I published four interval throwing programs built on workload data, ranging from 6 weeks to 7 months. I break down how I pick the right one in this post on interval throwing programs.
O’Driscoll SW et al. Am J Sports Med 2005;33(2):231-239. doi.org/10.1177/0363546504267804
Dugas JR et al. Am J Sports Med 2025;53(3):525-536. doi.org/10.1177/03635465251314054
To Tommy John or not…that is the question
Wrapping it up, I’d just like to add that there are probably many more scenarios that could play out. My goal was to give you some sort of framework and guidelines for someone presenting with a medial elbow issue and looking for answers.
The cluster of tests seems to be pretty straightforward and simple to understand, hopefully! There are a bunch of possibilities but Tommy John issues should be diagnosed with a good history and careful examination…good luck!
My recorded webinar on getting throwers back after Tommy John. Timelines, the throwing program and the mistakes I see most often. Use code LENNY to save on a yearly MedBridge subscription.
Watch the Course →
Evidence based sports rehab content, course updates and clinical pearls. No spam.
How to Progressively Load the Rotator Cuff
The rotator cuff is small, but it is not weak. How we progress rotator cuff strengthening with load, pauses, volume and position, from the Ask Mike Reinold Podcast.
Read Post →
4 Interval Throwing Programs: Matching the Program to the Injury
Our new IJSPT paper gives you four interval throwing programs, 6 weeks to 7 months, built on workload data. Here is how I match each one to the injury.
Read Post →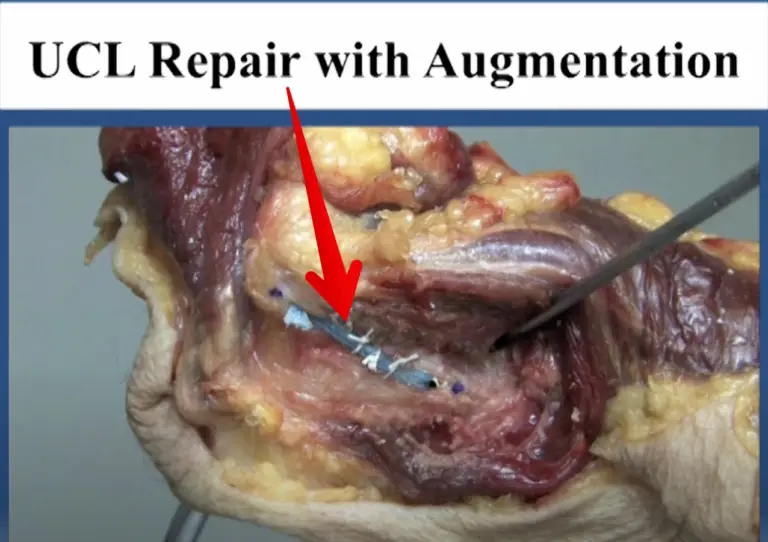
Diagnosed with an elbow UCL Tear- Reconstruction or Internal Brace surgery?
Diagnosed with a UCL tear? A plain English look at Tommy John reconstruction vs the internal brace, return to play times, and what the evidence says.
Read Post →
Comments
9 responses to “UCL Tests: How I Test the Elbow for a UCL Sprain in Baseball Players”
Good stuff as always, thanks Lenny.
Thanks Greg!
Thanks Greg!
Great read and right to the point! I like hearing your experience with seeing tons of elbows where I see very little where I practice. Keep up the good work and give Brooks “Calvin” Klein a hard time for me!
Thanks Skyler… appreciate the comment.
Hey Lenny, Thanks for the article/video. What are the names of these tests for documentation purposes?
the names I use are in the post… Milking sign or dynamic milking sign and valgus extension overload (either seated or supine)…along with probe valgus test. Hope this helps.
What are the most common sites of pain location if UCL is involved?
Joseph, pain along the medial epicondyle and sublime tubercle with late cocking or stretching the shoulder into external rotation. May also have tingling into 4-5 fingers from ulnar nerve irritation. Hope this helps.